Dr. Jung Su LeeDirector, UVOM Plastic Surgery

Foreign material removal

UVOM Plastic Surgery has used endoscopy to remove forehead implants and foreign materials since 1999. Under-eye foreign material removal is performed exclusively by Dr. Chang Min Kang at UVOM Plastic Surgery.

Medical Director Dr. Jung Su Lee uses ultrasound to assess the depth and distribution of foreign material, fibrosis, and granulomas before deciding the extent of surgery. In areas close to nerves and blood vessels, such as the forehead, glabella, and temples, he uses an endoscope to view surrounding structures during the procedure. As with revision surgery, structures altered by previous procedures must first be identified. If repeated injections have placed material in several tissue layers, some may remain or staged surgery may be necessary.

This surgery addresses implants, fat, fillers, or unapproved materials put into the face years earlier that have hardened or become inflamed: examinations first pinpoint where they are, and the material is then taken out while viewed directly.

What is removed?
Injected materials that lack approval, non-dissolvable fillers, grafted fat that is excessive or has hardened, and forehead and temple implants.
How are they assessed?
Ultrasound reveals how deep the material lies and how it is spread, and CT detects hardened regions and bone changes.
How are they removed?
Depending on how soft or hard the material is and how strongly it is attached to nearby tissue, the method chosen may be an incision, endoscopy, ultrasound equipment, or a fine cannula.
Can everything be removed?
Removing 100% is difficult since nerves and normal tissue have to be protected. The focus is on reducing the regions responsible for pain, inflammation, and deformity.

How this compares with conventional methods

Conventional methods

If filler becomes lumpy or leads to swelling, the usual first step is a dissolving injection. Steroids may be injected to calm inflammation, and the material may also be squeezed out or suctioned with a needle or fine cannula.

Limitations

Only hyaluronic acid fillers respond to dissolving injections. Fillers made of other ingredients, such as Ellansé or Artecoll, as well as grafted fat and unapproved materials, are not dissolved by them. Steroid injections ease swelling and inflammation, yet the material behind the problem stays in place, so issues may return over time.

Once material has hardened with time or stuck to the tissue around it, removing it without direct sight is difficult. Some may be left behind, or normal tissue may be damaged in the process.

Dr. Lee's approach

The first step is ultrasound and CT to determine where the material is, how deep it lies, and how much there is. The technique is then chosen based on its state. A fine cannula removes soft material that is only slightly adherent, while ultrasonic vibration detaches material that is stuck. In the forehead, temples, and glabella, where nerves are abundant, an endoscope gives a magnified view; hard lumps are taken out through an incision while seen directly.

Because the treated area may become sunken or the skin may droop, how it will look after removal is planned beforehand.

Benefits and precautions

Working under direct visualization makes it possible to reduce the problematic material selectively while sparing normal fat as well as nerves and blood vessels. Locating it in advance helps prevent dissection that is wider than necessary.

The aim is not total removal. Removing too aggressively can lead to depressions or nerve damage, so part of the material may be left or the surgery may be done in stages. Recovery generally takes 1 week or more, and follow-up of the under-eye area lasts 6 months or longer.

Glossary

Hyaluronidase
A medication given by injection to dissolve hyaluronic acid fillers. Fillers made of other ingredients do not respond to it.
Foreign-body granuloma
A hard inflammatory nodule that develops as the body walls off foreign material.
Adhesion
A state in which tissues that should remain apart become attached to each other.
Calcification
Deposits of calcium in tissue that make it turn stone-hard.
Ultrasound examination
A test in which a probe on the skin shows the tissues beneath it on a screen. It reveals how deep and how widespread the material is.

Types of material

Treatment varies with the material. Hyaluronidase dissolves fillers made of hyaluronic acid only. Semipermanent fillers composed of collagen or calcium are not broken down by it and are taken out surgically.

CategoryExamplesCharacteristics
Illicit foreign materialsCandle wax, paraffin and silicone of industrial grade, petroleum jelly, oils, and illicit collagen or fillersNone of these materials is approved. They have a strong tendency to stick to tissue, and even in the absence of symptoms, delay makes chronic inflammation, necrosis of the skin, and granulomas more likely.
Permanent fillersAquamid, Royamid, PerformSkin necrosis and infection may develop. When an inflammatory reaction is present, removal may come after a course of medication.
Collagen-stimulating fillersEllanséA filler that combines PCL with CMC. When collagen forms beyond what is expected, it can become hard along with the cells around it.
PMMA fillersArtecoll, ArtefillThis ingredient is also found in artificial bone. With time, it can create hard lumps that are extremely difficult to remove. Endoscopy or direct incisions suit it better than a cannula.
Calcium fillersRadiesseThey tend not to migrate much, which is an advantage, but their firm adhesion to tissue makes them hard to remove.
Hyaluronic acid fillersWhen they are not dissolved by hyaluronidaseMost dissolve with injection, though long-present filler or advanced fibrosis may need surgical removal.
Grafted fatOil cysts, fibrosis, calcification, and excessive retention of the graftSymptoms can appear over time, and if weight increases, the grafted area may look out of proportion and enlarged.

Fillers listed by UVOM Plastic Surgery as non-dissolvable and as candidates for surgical removal

RadiesseEllanséArtecollArtefillSkinPlus HYALAestheFillSculptraAquamidPerformAquafillingJuvelookUltraCol

Diagnosis

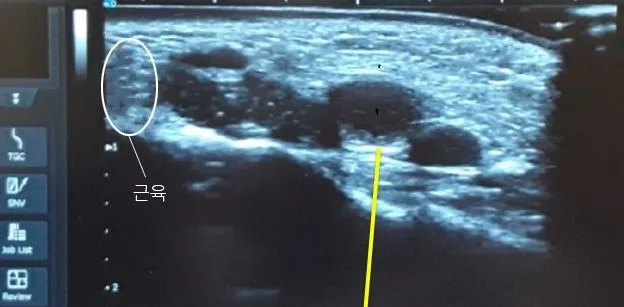
Ultrasound before surgery reveals the true depth and distribution of the foreign material. This allows it to be removed precisely while limiting needless dissection and damage to normal tissue.

3D CT reveals where calcification and cysts are and how extensive they are. If a hard lump following fat grafting shows bone density on CT, it is calcified. In the case of forehead implants, CT evaluates their position and size and any erosion of the bone.

Where necessary, removed tissue undergoes microscopic examination. This may reveal inflammation, firm lumps, or hardened tissue surrounding the foreign material.

Under-eye ultrasound image showing the location of muscle and foreign material

Removal methods

There is no one technique that removes all types of foreign material. The choice depends on firmness, adhesion, and location, and techniques are combined as needed.

When material is soft with little adhesion

Removal with a fine tube (cannula)

When the material is soft and only slightly adherent to nearby tissue, its exact position is located with ultrasound, and a fine cannula is then inserted to take it out without an incision.

When material adheres to surrounding tissue

Ultrasound-assisted removal

The material is detached from surrounding tissue by ultrasonic vibration and then removed. Surplus grafted fat is liquefied selectively and taken out evenly, so an uneven skin surface is unlikely.

Forehead, glabella, and temples

Endoscopic removal

Nerves are abundant in these areas, and motor nerves run from the temples to the forehead. Removal is done at 20-fold magnification with nerve tissue preserved. Placing incisions inside the scalp makes scars less visible.

When material has hardened

Removal through an incision

Granulomas and hardened foreign material are taken out under direct visualization. Near the eyes and nose, removal is paired with related surgery so fewer incisions are needed; in the lip and deep-cheek regions, incisions are made inside the mouth so scars are not visible.

When a filler is non-dissolvable, laser and comparable methods remove less of it. Operating through an incision or with an endoscope lets the amount be assessed directly, which helps take out a considerable quantity safely and lowers the risk of injury to vessels and nerves.

Approach by area

Incisions are placed in existing surgical scars or discreet sites.

AreaApproach
Around the eyesThe incision is placed under the eye or below the eyebrow. Where appropriate, upper or lower blepharoplasty or repositioning of under-eye fat may be performed at the same time. A small opening is enough to remove some materials.
NoseMaterial is removed through an open approach while the structures are protected. To prevent contracture, in which shrinking tissue can pull the nasal tip upward, cartilage grafting is used.
LipsAdherent masses, nodules, and scattered foreign material are removed through an incision on the inner side of the lip.
ForeheadEndoscopic removal is carried out through a scalp incision above the hairline. In some cases, a cannula is used.
Cheeks, deep cheek areas, and nasolabial foldsA cannula removes foreign material lying in the subcutaneous fat layer, while material in the deep cheek is taken out through an intraoral incision.
ChinRemoval is done with a cannula or through an incision in the skin under the chin. Material lying deeper is reached via an incision inside the mouth.
When skin necrosis has progressedBecause the tissue being operated on is already damaged, treatment with fat-derived regenerative cells (SVF) at the same time may be considered depending on the condition.

Under-eye foreign material removal

At UVOM Plastic Surgery, only Medical Director Dr. Chang Min Kang performs removal of foreign material from the under-eye area.

Skin under the eyes is thinner than elsewhere, so foreign material there is more readily seen and felt. Many nerves and blood vessels run through the muscle, and the foreign material may be tangled with them. To avoid lower eyelid retraction, in which the lower eyelid is pulled down, or ectropion, in which it turns outward, the operation has to take into account how the foreign material relates to normal structures.

A single lump felt from the outside may turn out during surgery to be several capsules of varying size lying among the fibers of the orbicularis oculi muscle. After encapsulation has formed, material is more likely to be left behind when removal is done without an incision. Leftover material shows more under the eyes than in other areas, so taking out a considerable amount via an incision is preferred.

If needed, the lower blepharoplasty approach allows foreign material to be removed while under-eye structures are corrected as well. When material has spread widely between skin and muscle, removing all of it in a single operation can be difficult, and some may be left. Removing too much may lead to hollowing or change the shape of the lower eyelid. Patients frequently cannot recall the product names of injections given years or decades earlier, and ultrasound may not be able to pinpoint the exact composition of fibrosis and old mixtures. In these situations, diagnosis and treatment are carried out together while the response to hyaluronidase is evaluated. When pain, deformity, and inflammation do not resolve, surgery along with tissue examination is considered.

Removal methods

  • Non-incisional approach Soft material lying close to the under-eye area is liquefied selectively and taken out through a small opening.
  • Transconjunctival incision Appropriate where there is limited skin laxity and the material lies close to the eye.
  • Skin incision Chosen when the material is hard, when skin laxity requires correction, or when it lies farther away from the under-eye region, for example the anterior cheek, the cheekbone, or the tear trough.
ItemUnder-eye foreign material removalGrafted fat removal
Operating timeWithin 90–120 minutesWithin 60 minutes
AnesthesiaSedationSedation
Suture removalAfter 5–7 daysIf sutures were placed, after 7 days
Follow-up treatment visits1–2 visits1–2 visits
Hospital admissionNot requiredNot required
Recovery periodAfter approximately 1 weekAfter approximately 1 week

These general guidelines from UVOM Plastic Surgery may differ depending on the patient's condition and the surgical method used.

Inflammation

Under-eye swelling, warmth, and pain

Deformity

Irregular contours beneath the eyes, or a lower eyelid that turns outward

Visible foreign material

Injected substance visible through the skin or palpable

Adverse reactions

Skin that peels or weeps, or hard lumps that can be felt

Skin necrosis

Compression of blood vessels makes the treated site turn bluish, or blisters form and the tissue dies

Distinguishing it from under-eye fat

They cannot be told apart by look or feel alone; the assessment relies on the patient's procedure history, an in-person exam, and high-frequency ultrasound.

Removal of grafted fat

Problems after fat grafting may appear gradually. When a large amount is grafted in a single session, the weight of the fat cells can lead to sagging. If the patient gains weight, the grafted fat cells may grow larger, leaving that area looking out of proportion and bulky.

SymptomDescription
Excessive graft retentionOver-grafting leads to a look that is unnatural or asymmetric.
Oil cystsWhen the core of the grafted fat is cut off from its blood supply and undergoes necrosis, a cyst may develop. This cyst is filled with oil and feels hard, similar to a nodule.
Inflammation and infectionPostoperative swelling is excessive and lasting, with heat and edema.
CalcificationCalcium from the blood is deposited in the tissue, leaving it firm and irregular. In severe cases, nearby nerves become irritated, which causes pain.
Fat necrosisGrafted fat that does not survive may lead to infection of the skin and tissue necrosis, possibly discoloring the skin's surface.

Extent of removal

Fat is not simply removed wholesale, because the tissue around nerves and muscles has to be taken into account. Where it is not palpable by hand, it is better not to take out too much. Overly aggressive removal risks damaging tissue, nerves included.

Timing of further removal

For roughly 3 days following removal, swelling and bruising build up, and then they start to subside. Past an intermediate stage of 6–8 weeks, the swelling keeps going down for as long as 6 months. Should more removal be required after that point, another procedure can be performed.

Forehead implant removal

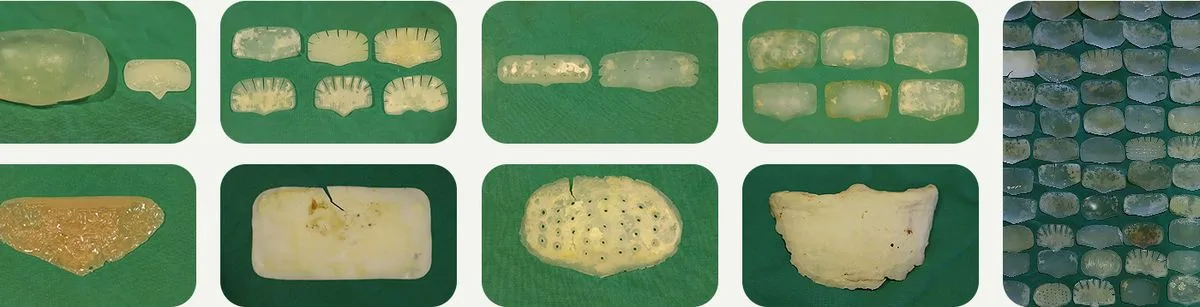
Many forehead implants are made to order to match the shape of the individual's forehead. They can be made from silicone, bone cement, Gore-Tex, or AlloDerm, among other materials, and size and shape differ even between implants of the same material. Since 1999, UVOM Plastic Surgery has removed forehead implants endoscopically.

When is removal of an old forehead implant considered?

Various forehead implants removed at UVOM Plastic Surgery

Surgical principles

  • Reuse the prior incision. To avoid creating new scars, access is made through the earlier surgical site. When more incisions are required, 1–3 openings of roughly 2–3 cm each are made.
  • Take out bony projections. Bone may grow through the small perforations in a silicone implant. Any projections of bone that would be palpable after surgery are taken out. A bump of roughly 1 mm is masked by the thickness of the skin and is not palpable.
  • Double-check. Right after removal, the implant's shape is inspected. If any part is torn or missing, the endoscope is used a second time to look for fragments left behind.
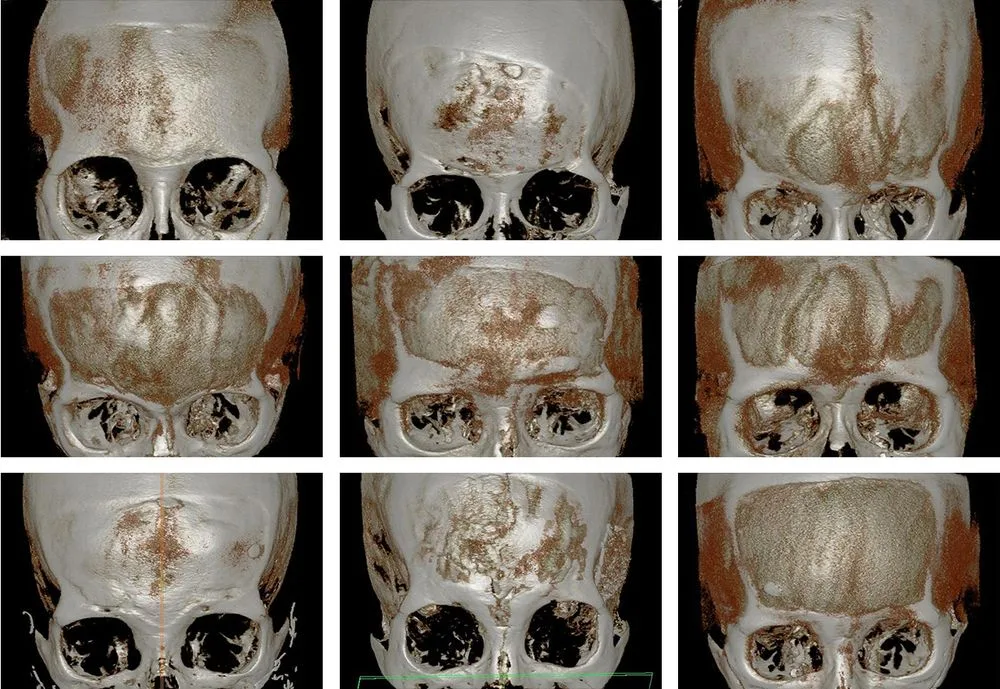
3D CT of a forehead implant

Before surgery, CT shows where the implant sits, how large it is, and where the nerves exit. Because bone erosion may occur as time passes after implant surgery, the possibility of a hollow forehead once the implant is out is planned for in advance.

When removal is considered

  • Blood pooling or a hematoma
  • Ongoing headaches or a sense of a foreign body
  • Implant displacement causing asymmetry
  • An artificial look, or an implant edge that shows
  • When considering a forehead lift

Procedures considered together

  • Endoscopic forehead lift Performing a lift while the implant remains in place raises the chance of displacement-related complications. When removal and lifting are done together, the space already dissected is put to use, cutting down on unnecessary dissection.
  • Forehead fat grafting Once the implant is removed, there may be volume loss or contour irregularities resulting from bone erosion. Grafting fat is advised 6 months after surgery.

Limitations and recovery

Is 100% of the material removable with surgery?

Because normal tissue has to be preserved, removing 100% is difficult even surgically. Still, foreign material that has adhered to tissue can be taken out under direct or endoscopic vision, and hardened granuloma masses can likewise be excised while blood vessels, nerves, and muscles are protected.

Is recovery immediate after surgery?

For 48–72 hours postoperatively the swelling grows, after which it slowly goes down. Recovery differs between patients, but daily routines can usually be resumed after 7 days on average. Where bruising is severe, 2 weeks or more may be needed.

Does the under-eye area swell more?

The swelling is greatest on the second day. An ice pack laid on top of clean gauze can be helpful. Because scar tissue may leave the skin irregular, the tissue can take longer to soften compared with other cosmetic procedures. Follow-up is advised for a minimum of 6 months as the swelling and bruising resolve.

Is surgery the only way to remove semipermanent fillers?

Surgery is not in every case the only option. A method without incisions may work after 1 session, though a 2nd or 3rd session may be required. Since filler causing problems should ideally be taken out without delay, the approach is chosen based on the condition.

Why use an endoscope to remove filler?

The forehead, temples, and glabella are treated endoscopically. Numerous nerves run through these regions, including motor nerves that travel from the temples to the forehead. Because damage along a nerve's path can result in paralysis, the endoscope is used so that nerve tissue can be preserved during removal.

If I don't know what the material is, can I continue getting dissolving injections?

When lumps and a foreign-body sensation persist despite a sufficient course of dissolving treatment based on a clinician's diagnosis, it may be worth considering surgical removal. Where leftover foreign material leads to repeated inflammation and deformity, removing it while directly visualizing the material and the changed tissue is an option to consider.

After my forehead implant surgery, blood pooled and was drawn out using a syringe. Must the implant be removed now?

Once the pressure or headache goes away, it may be possible to monitor the situation for some time. Removal is still advised, though, since the pooling of blood frequently comes back. It arises because bone erosion opens a gap between the implant and the forehead bone, and that gap may grow larger.

Can hot compresses be used after surgery?

It is not advised. Because sensation is diminished at the surgical site, there is a risk of burns. Apply cold compresses over 2–3 days; after that, a half-body bath in warm water is advised to support circulation and lymphatic drainage.

Is removing all facial foreign material in one go the best approach?

No. Attempting to take out every bit of material that has spread through multiple layers or intermingled with normal fat, muscle, and nerves may raise the risk of depressions, changes in function, and nerve injury. It may be safer to address first the areas producing pain, inflammation, and deformity, to leave part of the material, or to divide the surgery into stages.

What is evaluated by ultrasound and by CT?

With ultrasound, the position and depth of material within soft tissue, fluid-related changes and nodules, and how these relate to neighboring tissue can be seen in real time. CT is helpful for evaluating the position of bone, calcification, prior facial contouring surgery, and widespread deformity. Which examinations are required depends on the symptoms and surgical history.

Is starting with dissolving injections an option?

Where hyaluronic acid filler has been confirmed or is strongly suspected, hyaluronidase may be the first option considered. Old mixtures, lumps from fat grafting, fibrosis, and granulomas, however, may show only a limited response. Re-evaluating the tissue layer that holds the material, along with the state of inflammation, is important before injections are repeated. When hyaluronic acid is confirmed and the issue can be resolved with dissolving injections, there is no rush to operate.

Why might sagging of the face increase once foreign material is taken out?

When material that has occupied facial volume for an extended period is removed, empty space and surplus skin can remain. Where the fat and SMAS have already descended, the sagging may be more noticeable once removal is done. For this reason, the volume that will remain and the supporting layers are evaluated beforehand.

Is it possible to have foreign material removal and a facelift in a single day?

In some cases, though it does not suit every patient. The evaluation covers active inflammation, risk of infection, how far the material extends, blood supply to the skin, and the expected dissection. When localized material is to be removed, considerable sagging is anticipated afterward, and inflammation is stable, a combined operation may be considered. When the risk is high, the surgery is done in stages.

Care after removal

For laxity of the skin and muscle resulting from foreign material, a thread lift, facelift, or forehead lift may be considered, depending on the area. Hollow or irregular areas left after removal may be improved with fat grafting. Ultrasound lifting is advised 3 months post-surgery. What is recommended differs with age and area.

See the population, methods, results, and limitations of each study

Supporting evidence

Recovery course

TimingTypical course
2–3 days after surgeryThis is when swelling is most pronounced. Under-eye swelling is greatest on the second day; cold compresses can be helpful.
5–7 days after surgeryIf an incision was made under the eye, the stitches come out. On average, normal daily activities can usually be resumed after 7 days.
2 weeks after surgerySevere bruising may need this long to resolve.
6–8 weeks after surgeryA middle stage in which the swelling continues to go down steadily.
3 months after surgeryTreatments like ultrasound lifting become possible.
6 months after surgeryMost of the swelling has resolved, and the need for additional removal is evaluated. The under-eye area is followed for 6 months or more.

This can differ depending on each person's condition and how extensive the surgery is.

Patient reviews

Removal of grafted fat from the forehead, cheeks, and chin

Gangnam Unni review · June 2026

About 3 years ago, I had fat grafted to my forehead, cheeks, and chin, and I had it removed. My eyes also looked heavy, so I had incisional ptosis correction at the same time. The fat removal came first, followed by the eye surgery. Dr. Jung Su Lee removed the fat, and another medical director performed the ptosis correction. Quite some time has passed now, and my forehead and chin hardly hurt and look much more natural. My cheeks still hurt a little, so it feels too early to say I have fully recovered. They are much better than at first, but it is still uncomfortable when they sometimes hurt while I smile, wash my face, or touch it. Still, I am really pleased with the design. My face, which looked heavy and unnatural after fat grafting, has improved, and the overall contour looks much cleaner and more natural. I am now waiting for the cheek pain to improve a little more.

Grafted fat removal

Gangnam Unni review · September 2026

Dr. Jung Su Lee at UVOM Plastic Surgery is the best. Both my satisfaction after surgery and the pain are at the highest level.

These reviews were reproduced from Gangnam Unni with the authors' consent. Each reflects one person's experience, and results vary.

Questions answered by Dr. Lee

Questions answered directly by Medical Director Dr. Jung Su Lee in the Doctor's Columns.

Is every firm filler lump a granuloma?

No. Overfilling, uneven filler distribution, migration, fibrosis, infection, and delayed inflammatory nodules can all feel firm. A granuloma cannot be definitively diagnosed by touch alone.

Answered by Medical Director Dr. Jung Su Lee · What is a filler granuloma? How it differs from filler clumping, its symptoms, and treatment

Can hyaluronic acid fillers also cause granulomas?

Yes. Although hyaluronic acid fillers are biodegradable, delayed inflammatory reactions and foreign-body granulomas have rarely been reported. However, not every delayed nodule after hyaluronic acid filler injection is a histologically confirmed granuloma.

Answered by Medical Director Dr. Jung Su Lee · What is a filler granuloma? How it differs from filler clumping, its symptoms, and treatment

Can dissolving injections eliminate a filler granuloma?

Hyaluronidase may help when hyaluronic acid filler remains. However, it is ineffective for non-hyaluronic acid fillers, and additional treatment may be needed when fibrosis or granulomatous inflammation has already developed.

Answered by Medical Director Dr. Jung Su Lee · What is a filler granuloma? How it differs from filler clumping, its symptoms, and treatment

Can fillers injected long ago still cause problems?

Yes. Filler granulomas or delayed inflammatory reactions can appear months or years after injection. Problems may be discovered long afterward, particularly with materials of unknown composition or nonabsorbable substances.

Answered by Medical Director Dr. Jung Su Lee · What is a filler granuloma? How it differs from filler clumping, its symptoms, and treatment

Does a filler granuloma always require surgery?

Not always. Nonsurgical treatment may be considered first depending on the filler composition, presence of infection, lesion size and extent, and skin condition.

However, surgical removal may be considered for recurrent inflammation, skin damage, or a mass that does not respond to treatment.

Answered by Medical Director Dr. Jung Su Lee · What is a filler granuloma? How it differs from filler clumping, its symptoms, and treatment

Can surgery remove all the filler?

Whether removal is possible and how much can be removed depend on the type and location of material and the degree of adhesion to surrounding tissue.

Even a relatively localized lesion may be difficult to remove completely if it is closely attached to normal tissue or important structures such as nerves and blood vessels.

Rather than attempting to remove all filler indiscriminately, it is important to assess how much of the symptomatic lesion can be safely removed while minimizing normal tissue injury.

Answered by Medical Director Dr. Jung Su Lee · What is a filler granuloma? How it differs from filler clumping, its symptoms, and treatment

Can an area suddenly feel hard years after fat grafting?

It is possible. Small nodules or areas of fibrosis or calcification that were not previously noticeable at an old fat-grafting site may become palpable over time.

However, new firmness at a grafted site does not necessarily mean that the previously grafted fat is the cause.

If a lesion has only recently become palpable, other possible causes should also be checked.

Answered by Medical Director Dr. Jung Su Lee · Why does a fat-grafted area become hard?

Will massaging the hard area make it disappear?

Vigorous massage cannot be recommended before the cause is identified.

Unlike temporary symptoms during recovery, an established hard calcified mass is unlikely to resolve with massage alone.

In particular, avoid repeatedly pressing hard on painful or inflamed areas.

Answered by Medical Director Dr. Jung Su Lee · Why does a fat-grafted area become hard?

Can all grafted fat be removed in one procedure?

This depends on the lesion's form and extent.

If fat is spread widely across several layers beneath the skin or has become fibrotic and adherent to surrounding normal tissue, selective removal of the necessary areas may be required to preserve normal tissue.

For safe removal, ultrasound or CT may be needed to identify the remaining fat, calcification, and their relationship to surrounding tissue.

Firmness in a fat-grafted area does not necessarily mean that a complication has occurred.

Temporary firmness can occur during early postoperative recovery.

However, if a distinct lump remains for several months or becomes firmer over time,

if the grafted area is visibly apparent through the skin, develops uneven contours, or becomes painful, identifying the cause may be necessary.

After considering when, where, and how many times fat was grafted, together with the current tissue condition,

whether treatment or removal is actually needed should be determined individually.

If a hard lump in a fat-grafted area concerns you, we recommend assessing the fat and surrounding tissue through a consultation at 02-545-3700 or via KakaoTalk at “UVOM Plastic Surgery.”

Answered by Medical Director Dr. Jung Su Lee · Why does a fat-grafted area become hard?

Is fat grafting always needed after forehead implant removal?

No. If the original forehead contour and soft-tissue volume remain adequate after removal, fat grafting may not be necessary.

Implant removal and fat grafting therefore do not always need to be performed together. The need for fat grafting should be assessed separately based on the expected contour and actual tissue condition after removal.

Answered by Medical Director Dr. Jung Su Lee · Can fat grafting be combined with forehead implant removal?

Is the space left by the implant simply filled with fat?

No. An implant is a solid object of a defined shape and volume, whereas autologous fat is distributed within tissue and must survive after grafting. They create volume differently.

Rather than filling the implant's former space with an equal amount of fat, grafting is planned according to where volume is needed and the overall forehead contour after removal.

Answered by Medical Director Dr. Jung Su Lee · Can fat grafting be combined with forehead implant removal?

Is recovery faster if implant removal and fat grafting are performed together?

Not necessarily. There may be a practical advantage to performing both treatments in one operation, but recovery varies with the extent of removal, adhesion, fat harvest site, and extent of grafting. Currently available evidence does not support a general claim that simultaneous treatment produces faster recovery than staged treatment.

Answered by Medical Director Dr. Jung Su Lee · Can fat grafting be combined with forehead implant removal?

When can fat grafting be performed after forehead implant removal?

There is no single interval appropriate for everyone, but we generally recommend waiting at least 6 months. Timing should be determined after assessing inflammation or infection around the implant, the extent of removal, swelling and tissue recovery, and the actual remaining contour.

Answered by Medical Director Dr. Jung Su Lee · Can fat grafting be combined with forehead implant removal?

Can fat grafting reproduce the same forehead shape as an implant?

Autologous fat can improve insufficient forehead volume and curvature, but implants and fat grafts have different characteristics.

An implant has a fixed shape and volume, whereas grafted fat undergoes survival and resorption. The same projection and shape as the implant therefore cannot be guaranteed.

Answered by Medical Director Dr. Jung Su Lee · Can fat grafting be combined with forehead implant removal?

Can hyaluronic acid filler remain for at least 5 years?

Persistence varies with the product, injection site and amount, cross-linking properties, and individual tissue condition. Disappearance of visible volume does not necessarily mean that all filler-related residue or surrounding tissue reactions have resolved. However, a lump discovered at least 5 years after injection is not necessarily residual hyaluronic acid filler. Examination and appropriate tests may be used to distinguish residual filler, fibrosis, inflammatory nodules, and other masses.

Answered by Medical Director Dr. Jung Su Lee · Can granulomas appear years after filler injections?

Could a granuloma be related to filler injected 10 years ago?

The possibility cannot be completely excluded. Case studies of oral and facial foreign-body granulomas have reported filler injections approximately 3–10 years before the lesions were identified.

However, those studies also included non-hyaluronic acid fillers and mixed treatments. This does not mean every new lump appearing 10 years after injection is a filler granuloma. Other soft-tissue masses must be distinguished.

Answered by Medical Director Dr. Jung Su Lee · Can granulomas appear years after filler injections?

Do granulomas feel hard?

They can feel firm, but touch alone cannot confirm a granuloma. Residual filler, fibrosis, infectious nodules, and other masses may also feel firm.

Answered by Medical Director Dr. Jung Su Lee · Can granulomas appear years after filler injections?

Can a filler granuloma be painless?

Yes. Active inflammation may cause pain, redness, and swelling, but some present only as a palpable lump without pain. Painless palpable nodules were also commonly reported in case studies of oral and facial foreign-body granulomas.

Answered by Medical Director Dr. Jung Su Lee · Can granulomas appear years after filler injections?

Does dissolving the filler make a granuloma disappear immediately?

Hyaluronidase may help if the causative material is hyaluronic acid and residual filler is a major contributing factor.

However, hyaluronidase is an enzyme that breaks down hyaluronic acid; it does not directly remove infection, fibrosis, or all established granulomatous inflammatory tissue. Repeated or other treatments may be needed depending on the lesion.

Answered by Medical Director Dr. Jung Su Lee · Can granulomas appear years after filler injections?

Can the problem be diagnosed if I do not know which filler was used?

Even without the product name, the cause can be narrowed down using the timing, sites, and number of treatments, changes in symptoms, an in-person examination, and imaging.

Repeated treatment with different fillers can complicate diagnosis and treatment. A biopsy may be considered when the cause is unclear or another condition must be distinguished.

Past filler treatment history matters even years later

Delayed inflammatory nodules and foreign-body granulomas related to fillers are uncommon complications, but may appear months to years after treatment. A firm lump, recurrent swelling, redness, or pain at a previously injected site warrants assessment of a possible connection, even if treatment was long ago.

However, not every late-developing lump is a foreign-body granuloma. Residual filler, migration, noninflammatory nodules, infection and abscesses, fibrosis, and unrelated soft-tissue masses can look similar.

Treatment should therefore be chosen after identifying the cause through procedure history, an in-person examination, and, when needed, imaging, culture, or biopsy, rather than dissolving filler or administering anti-inflammatory injections based on symptoms alone.

If facial foreign material or a filler granuloma concerns you, please call 02-545-3700 or contact “UVOM Plastic Surgery” on KakaoTalk.

For more columns on facial foreign material removal, click a title below ▼

How can an old facial injection be assessed when its ingredients are unknown?

I have been told that old filler remains. Can it all be removed?

Why tissue around facial foreign material becomes hard

Answered by Medical Director Dr. Jung Su Lee · Can granulomas appear years after filler injections?

Can fat that has survived in the face be removed again?

Depending on the condition, some can be reduced or removed. However, grafted fat may survive across several layers among normal tissue, so complete removal of only the grafted fat cannot be assured.

Answered by Medical Director Dr. Jung Su Lee · Does your face look larger after facial fat grafting? Can the grafted fat be removed?
Can facial fat grafts be removed with liposuction alone?

Limited liposuction may be considered when fat is relatively soft and evenly distributed. However, liposuction alone may be insufficient if the fat has formed hard lumps or is accompanied by fibrosis, adhesions, or fat necrosis.

Answered by Medical Director Dr. Jung Su Lee · Does your face look larger after facial fat grafting? Can the grafted fat be removed?
If my face looks larger immediately after surgery, should the fat be removed right away?

Early enlargement may be due to swelling, so excessive graft retention cannot be determined immediately. The timing of surgery and recovery should be reviewed, and swelling distinguished from surviving grafted fat before deciding on correction.

Answered by Medical Director Dr. Jung Su Lee · Does your face look larger after facial fat grafting? Can the grafted fat be removed?

Can fat-dissolving injections dissolve grafted fat?

They cannot be regarded as an established general standard treatment for overcorrection after facial fat grafting. Even small volume differences in the face can cause depressions and asymmetry, so the medication's approved indications, supporting evidence, and the condition of the fat must be assessed carefully.

Answered by Medical Director Dr. Jung Su Lee · Does your face look larger after facial fat grafting? Can the grafted fat be removed?

WhatsAppAsk a question